Oocytelarge

Old ovaries, new eggs? Hatching a debate

Can adult women make new oocytes?

by Sarah C.P. Williams

For decades, biology textbooks have stated this as fact: “Women are born with all the eggs, or oocytes they will ever have.”1 The assumption — which shapes research on infertility and developmental biology, as well as women’s mindsets about their biological clocks — is that as women age, they use up those reserves they are born with. With each menstrual cycle, egg by egg, the stockpile wears down.

But is it true that women can’t produce any new oocytes in their adult life? Over the past decade, some scientists have begun to question the long-held assumption, publishing evidence that they can isolate egg-producing stem cells from adult human ovaries.

Last week, biologist Allan Spradling of the Howard Hughes Medical Institute and Carnegie Institution for Science, cast a shadow over those findings with a new analysis of the ovaries of adult female mice, which have similar reproductive systems to humans. By his measures of new egg formation, which he has previously studied and characterized during fetal development, there were no signs of activity in the adults.

“Personally, I think it’s quite clear,” says Spradling. “All the evidence has always said this. When oocyte development is going on, you see cysts everywhere. When you look at adults, you don’t see any.”

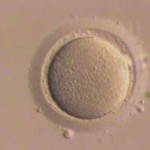
An oocyte, or egg cell, surrounded by some supporting cells.

The new paper does little to change the direction of those researchers already pursuing the stem cells, though. Jonathan Tilly of Massachusetts General Hospital was among the first to publish evidence that mice and human females have adult germ-line stem cells that can make new eggs.

“There’s so much evidence now from so many labs that have purified these cells and worked with these cells,” says Tilly. “What I don’t find of value is to say these cells don’t exist.”

For now, the two sides remain fractured — Spradling sees weaknesses in the way Tilly and others have isolated cells from the ovaries and suspects that the properties of the cells could change when they’re outside the body. And Tilly proposes that Spradling’s new data could be interpreted in a different way that in fact supports the presence of stem cells.

For women hoping for a scientific breakthrough to treat infertility — or even those simply curious about how their own body works — a consensus on the answer would be nice. But the continued probing on both sides may be just as much a boon to women’s health. After all, it’s questions like these that drive science forward.

In his new study, Spradling labeled a spattering of cells in the ovaries of female mice with fluorescent markers to make them visible and watched them as the mice aged. If any labeled cells were egg-producing stem cells, he says, they would spread the fluorescence as they made clusters of new eggs.

“But you never see clusters,” Spradling says. “Not once.”

In the process of this study, though, Spradling made new observations about how egg cells develop into their final form in female mice, published in a second paper this month. As the precursor cells to eggs mature, they lump together into cysts, a phenomenon also seen in the flies that Spradling has spent decades studying. In flies, one cyst eventually forms one egg. But in the mice, he discovered, those cysts break apart and form multiple eggs.

“This actually leads us to propose a new mechanism for what determines the number of oocytes,” says Spradling. And, of course, that means a better understanding of reproductive biology.

On the side of those who are confident about the existence of adult ovarian stem cells, the field of fertility medicine could be revolutionized if the cells that Tilly has isolated from ovaries can form healthy egg cells that can be fertilized in vitro. These stem cells could also be a tool to study more basic questions on oocyte development and formation or a screening platform for fertility drugs. Tilly is confident enough in the research that he has founded a company, OvaScience, to pursue the commercial and clinical potential of isolating the stem cells.

“The value for the lay public is that we have a new tool in our arsenal,” says Tilly.

Spradling doesn’t argue that continued research in this area isn’t a good thing. “Scientific knowledge doesn’t just come from the proposal of ideas, but also from their rigorous tests,” he says. “I think the most powerful tool we have in medical science is basic research,” he adds, referencing research using cell and animal studies. Investigations of the basics of how and when oocytes form, he says, are the best way forward toward developing ways to improve egg cell formation or development and could even lead to infertility treatments.

So if it finds support from further studies, Spradling’s new work — which states bluntly right in its title that “Female mice lack adult germ-line stem cells” — needn’t be seen as bad news for those dreaming of a breakthrough in understanding fertility. Instead, whether or not egg stem cells end up having clinical value, it’s a step forward in advancing understanding about women’s reproductive biology.

As Spradling puts it: “You have a much better chance of actually helping someone with infertility if you know what the real biology is. Right now, we’re a ways from really understanding the full biology, but we’re making progress.”

1 Direct quote from the third edition of “Human Physiology: An Integrated Approach”, one published by Pearson Education in 2004 and used in medical school classes. Continue reading

HIV+ doesn’t mean you can’t have children

Prenatal care and treatment access are big factors.

By Laura Newman

Last week, the media got all excited about the possibility of a cure for HIV perinatal transmission. What was lacking was the recognition that the public remains largely ignorant about HIV in pregnant women. Yet with good wellness care, prevention, HIV testing, and medication,HIV transmission from mother to child can be close to zero. The public needs to know that women who are pregnant and HIV positive can also live good-quality lives, as can their children.

CDCgraphicHIVThanks to Dr. Judy Levison, an obstetrician/gynecologist whose career centers on caring for HIV-pregnant women, I began to learn how scientific advancements in HIV-care make it possible for pregnant women with HIV and HIV-positive men to have children and not transmit the virus to their newborns. In the midst of this learning experience, I found out that a young woman I know, “Angela*,” was HIV positive and wanted to plan a pregnancy. I was shocked; I knew plenty of gay men with HIV, but rarely had I met a woman who had contracted the virus. Planning a pregnancy while being infected with HIV was something that I couldn’t imagine.

“Angela” is married and has lived with HIV for some years, with a low viral load by taking good care of herself and taking recommended antiretroviral therapy, when needed. She sought artificial insemination, one of several options available to HIV-affected couples. It worked. When she was planning her pregnancy, her parents were resistant. They worried that even though she is healthy now, that might change. They couldn’t imagine being saddled with taking care of a young child. Her parents’ resistance reminded me of the old coming-out stories we used to hear and how parents adapted to learning their child is gay. To their credit, both parents soon rose to the occasion. Angela and her spouse have a healthy toddler, and the grandparents love spending time with him.

Angela’s story isn’t everyone’s story. The hubbub at the recent 20th Conference on Retroviruses and Opportunistic Infections was not on the “functional cure” of the baby born to a pregnant woman with HIV, but on why, in this day and age, the mother doesn’t seem to have received the recommended prenatal care and antiretroviral therapy herself. Under what circumstances did she deliver? How did mom and baby get lost in the healthcare system? It’s far too easy to be captivated by a potential breakthrough and forget that plenty of people don’t get access to basic science-backed care that prevents HIV transmission in the first place.

As I describe below and as Angela’s experience illustrates, a lot of evidence shows that it is very safe for women with HIV to get pregnant, have healthy babies, and not transmit HIV to their children. Unfortunately, for many pregnant women with HIV, harsh judgments and inaccurate assumptions often carry the day. Let’s just say that HIV-positive moms and their kids have not earned the acceptance allotted to, say, a Magic Johnson, who has had HIV for decades, and with good HIV and wellness care, lives a good-quality life.

These inroads in science-based HIV prevention and care that have helped Johnson so much lag behind in poor and minority communities in the United States and low-resource countries around the world. HIV disproportionally affects African-Americans in the United States, and access to care, Medicaid cuts, and poverty reduce the chance that many people in need will receive good state-of-the-art prevention (regular testing, practicing safe sex, not sharing drug needles) and wellness care. Perinatal transmission could well rise in these communities.

Facing down ignorance

At first, being pregnant was not easy for Angela — not because her pregnancy was hard (it was not) — but because of the uneasiness some of her coworkers expressed about her becoming pregnant as an HIV-positive woman. Even though Angela worked in healthcare, some of her coworkers thought she had no business being pregnant. When she complained to her supervisor, the manager urged Angela to take it upon herself to educate staff about scientifically proven treatments for pregnant women with HIV that help moms stay well and prevent transmission to the baby. Angela asked instead for an in-service training, which was scheduled. Her colleagues’ attitudes turned around after the in-service.

It meant a lot to her to change the culture.

Angela had a normal term delivery, gave birth to a healthy baby, who is now a toddler, with no sign of HIV infection. Angela’s viral load remains undetectable. They are living healthy, high-quality lives like many other families, moms, and children.

The parents and prenatal planning

The ideal in the setting of HIV infection is that both partners are involved in preconception planning. Prevention of transmission of HIV from an HIV-positive father to an HIV-negative mom and fetus is now possible. The door is now open to HIV-positive men and women who want families but have HIV. Any plans they had to become parents have not simply vanished.

HIV research has advanced to the point that we now know that if HIV-positive individuals work with knowledgeable medical providers and have good access to proven practices, parents and children do quite well. Essential practices include:

  • Before trying to conceive, people should take antiretroviral drugs and have their infection under control, shown by a low viral load or undetectable levels of the virus (“undetectable” levels vary, depending on the lab) in their blood;
  • Couples are instructed to have unprotected sex only when the woman is ovulating. Current guidelines recommend using an ovulation prediction kit, which you can purchase at most drugstores.
  • Artificial insemination is another option that HIV-affected couples are using, as Angela did.
  • HIV testing is recommended routinely for all pregnant women, as well as for all non-pregnant adults and teens.
  • If a woman learns during her pregnancy for the first time that she is HIV infected, she can work with her healthcare provider to stay healthy, prevent mother-to-child transmission, and prevent passing HIV to her partner.


In general, people infected with HIV who are not pregnant begin taking anti-HIV medications when their CD4 counts fall below 500 cells/mm3 (HIV targets these immune cells and destroys them, compromising a person’s immunity). The medication regimen during pregnancy depends on whether or not you are taking medication to improve your own health or just your baby’s. In many cases, healthy women delay starting antiretroviral medication until the second trimester, which is when all women should be on HIV medication. However, HIV medication and interactions with other drugs and the fetus are complicated and require consultation with a physician. If women are diagnosed later in a pregnancy, they should start HIV drugs then. You can find detailed recommendations here.

During childbirth, women whose viral loads are still undetectable can have normal vaginal deliveries. However, according to the National Institutes of Health and other authorities, scheduled cesarean delivery at 38 weeks of gestation is recommended to reduce perinatal transmission of HIV for women with HIV-RNA levels >1,000 copies/mL or unknown HIV levels near the time of delivery, regardless of whether they were taking recommended antiretroviral drugs during pregnancy. The guidelines state that when there is a low rate of transmission (viral loads lower than 1000 copies/mL), the benefits of a scheduled c-section are unclear. Dr. Levison, an obstetrician/gynecologist at Baylor College of Medicine, Houston, TX, says that in her practice, women rarely need a cesarean section.

The newborn child

In the United States, breastfeeding is discouraged because HIV can be transmitted in breast milk. According to the Centers for Disease Control and Prevention (CDC), the risk for HIV transmission goes up as much as 45%. However, the topic of breastfeeding remains controversial. In healthy women with no HIV history, the broad consensus is that breastfeeding is best, giving babies excellent nutrition and helping the infant bond with mom. And many parts of the world have problems with sanitation and dirty water, making breastfeeding preferable to mixing formula. Outside of the US, according to Levison, in the UK, breastfeeding guidelines are more liberal. Furthermore, in some cultures, women are afraid not to breastfeed for fear that they will be outed as having an HIV infection, according to Levison, so many treating physicians adapt practice to the culture, preferences of the mom. Internationally, for example, in Africa, women often breastfeed and remain on antiretroviral drugs during that time. Formula is also costly. In the US, poor moms are eligible for formula through the federal Women’s Infants and Children’s nutritional support program.

Besides breastfeeding, HIV-positive moms need to know that pre-chewing of food before feeding baby is a transmission risk.

As soon as a woman goes into labor and during childbirth, the infantmust begin a six-week course of the antiretroviral medication zidovudine (AZT). Current guidelines also state that the baby should be tested for HIV at 14 to 21 days, at 1 to 2 months, and again at 4 to 6 months. If the viral load remains undetectable after two tests, the baby is considered to not have gotten HIV.

Resolving resource disparities

The moms, dads, and kids with HIV have enormous potential to live healthy lives for decades on proven antiretroviral drugs.

In fact, a December 2012 CDC Fact Sheet states that the number of women with HIV giving birth in the United States increased approximately 30% from 6,000 to 7,000 in 2000 to 8700 in 2006. During that same time frame, the estimated number of perinatal infections per year in all 50 states and 5 dependent areas continued to decline.

It’s not all good news, though, because of marked disparities in resource allocation and pre- and perinatal care. According to CDC data, 63% of perinatal infections were in blacks/African-Americans; 22% were in Hispanics/Latinos, and 13% were in whites. That leaves a lot of work to be done in enhancing targeted prevention programs.

Another recent milestone is that the US Preventive Services Task Force is finally about to endorse universal HIV testing, long after the CDC backed such a move in 2006. This milestone is important to because it is also linked to health reform. All public and private health plans are required to provide coverage for U.S. Preventive Services Task Force-recommended preventive services without patient copayments.

With this availability, perhaps women might learn about an HIV infection before they become pregnant, giving them time to have their own treatment in place before it is too late to protect the baby. The case report of the baby cured of HIV gives a lot of hope, but even more preferable would be preventing HIV infection in the first place, through safe sex and not exchanging needles. Once people become infected, for whatever reason, their lives should no longer be viewed as if they are at in a holding pattern until death.

The world needs to know that just like every other mom, dads and pregnant women with HIV can parent children, stay healthy, and not transmit the virus to their babies. Paramount in this is universal HIV testing for adults and teens, prevention programs, and ensuring scientifically proven treatment of the mother before, during, and after her pregnancy.

*Named changed to protect identity. Continue reading

